

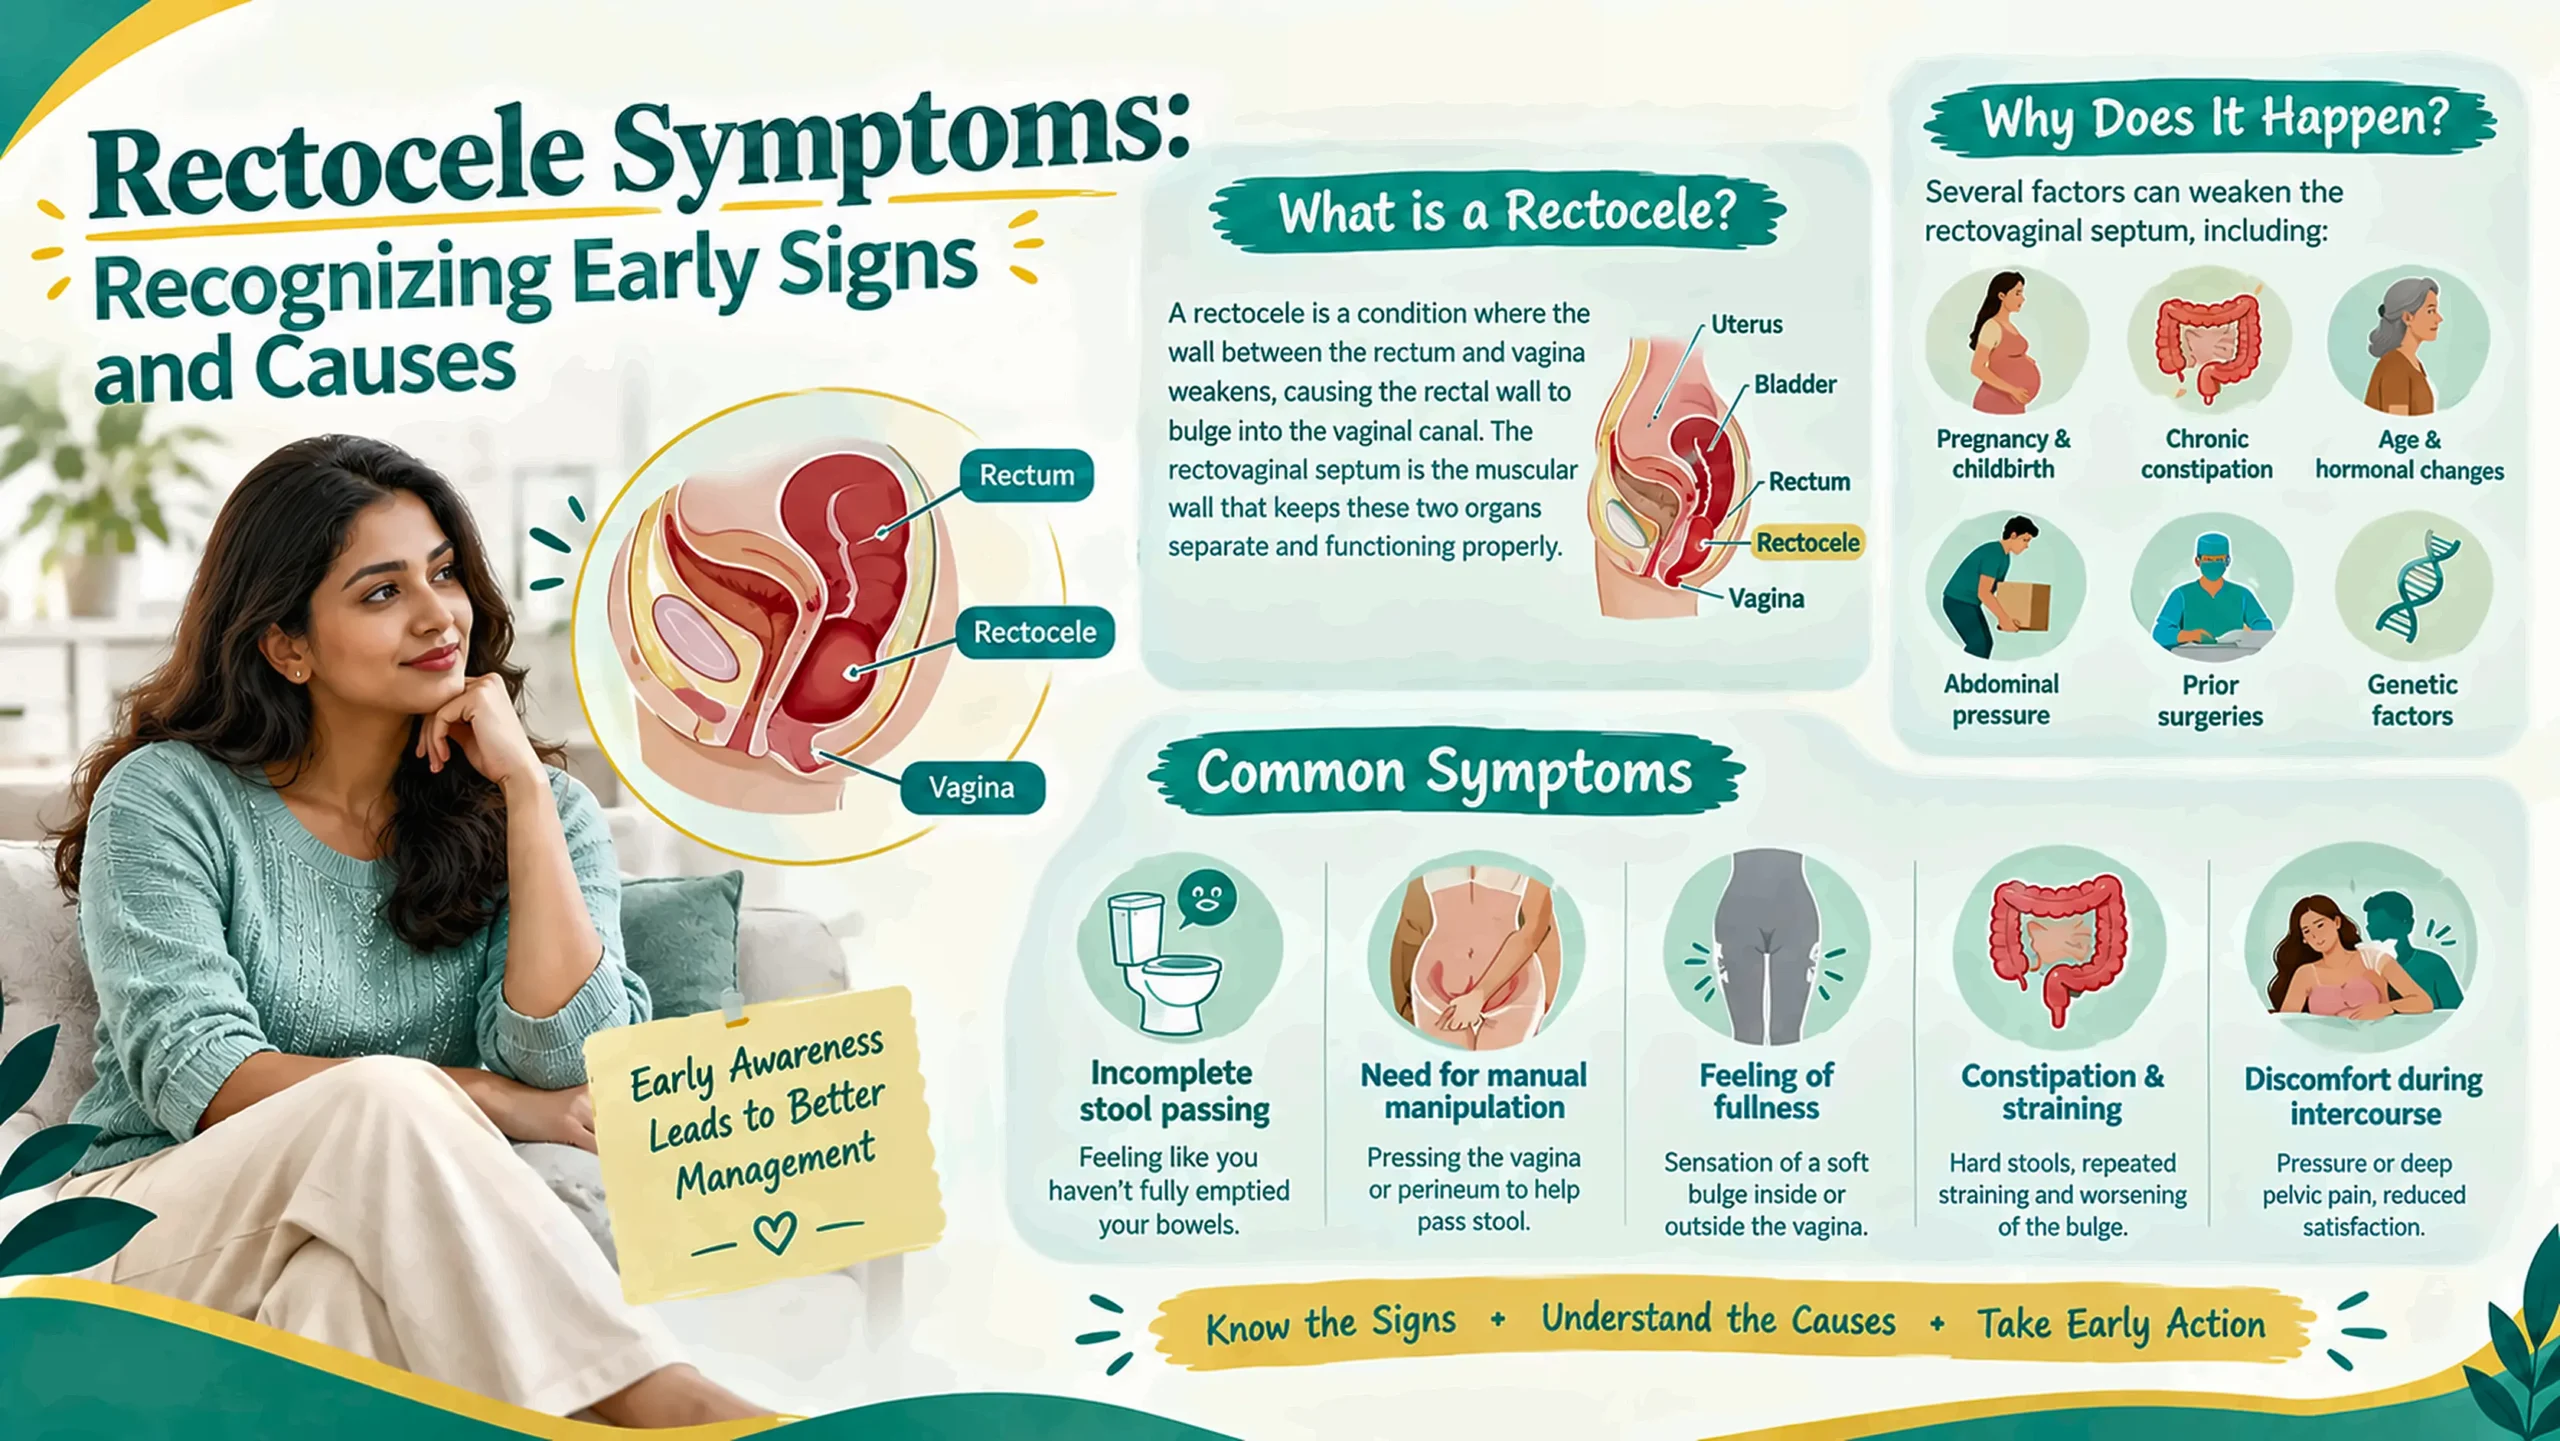
Rectocele is a condition where the wall between the rectum and vagina is compromised structurally and affects the functioning of both organs in women. The rectum and vagina are two organs present in the pelvic region in all women. They are present at the very base called the pelvic floor. These organs are separated by a muscular wall which functions to effectively separate the two organs. And while it may seem like this shared muscle—called the rectovaginal septum, only separates the two organs, it does much more and is needed for effective functioning of them. What happens when this muscle is compromised and how does one know it? This article will guide you all about this condition called rectocele, rectocele symptoms and why it is important to address it at the earliest.
What is a rectocele and how does the tissue between the vagina and rectum weaken?
- The rectum and vagina both have canal/tube-like structures which open to the outside of your body. They can be imagined as two tubes, parallel to each other, and sharing a common wall in between them.
- This muscular wall is called the rectovaginal septum, and runs vertically along with the vagina and rectum.
- It separates the back wall of the vagina and the front wall of the rectum.
- This septum is made of tough connective muscle tissue to keep it firm and separate the ending portions of both the rectum and vagina.
- When this septum loses its firmness or bulges into the vaginal canal, the condition is called a rectocele.
- A study done two years back in India— Indian J Obstet Gynecol Res 2024;11(4):612-616, reports that rectocele makes up almost a whooping high 52% of all cases of pelvic organ prolapse (changes in pelvic organs and their structures).
How do so many women face weakened rectovaginal muscles?
There are many reasons why this septum weakens, like:
- Pregnancy and vaginal childbirth: The intense physical strain and stretching during pregnancy and delivery—especially prolonged labor, or deliveries involving forceps or vacuum extractions, can tear or overstretch the connective tissue of the rectovaginal septum. Often, recovery does not happen optimally, making the septal wall weak.
- Long-term constipation: Consistently pushing or straining during bowel movements puts intense pressure on the rectovaginal wall. Over time, this repeated pressure can weaken the connective tissue, causing it to thin and bulge forward.
- Age and Hormonal Changes: As women age, especially after menopause, the body produces less estrogen. Lower estrogen levels reduce collagen production and loss of tissue elasticity. Since the septum is mostly connective tissue, it gets thinner, and weaker, and more prone to bulging out.
- Persistent pressure in the abdomen: Conditions that cause long-term downward pressure on the pelvis, such as a chronic cough, heavy lifting on a regular basis, or obesity, puts constant weight on the pelvic floor support structures. This results in them becoming weak from the repeated downward pressure.
- Prior surgeries: Surgical procedures like hysterectomy or prolapse repairs, can sometimes disrupt the connective tissues, making the r vaginal wall more vulnerable to weakening over time.
- Genetic factors: Some women naturally have weaker connective tissues, making their pelvic muscles more prone to stretching and bulging.
Why do women with rectoceles experience a feeling of incomplete bowel evacuation? – and other common rectocele symptoms
- Even with such high numbers (almost half of pelvic muscle change cases), not much is talked about it largely due to social awkwardness around the symptoms of rectocele.
- Since the rectovaginal septum is in between the rectum and vagina, all of the symptoms observed when a woman has this condition are either excretory related or sexual related symptoms.
- Both of the above functions are inherently talked about lesser due to social conditioning and awkwardness around these topics.
- However, this condition occurs very naturally to women, and a better understanding of the rectocele symptoms will help identify this condition at the early stages when non-interventional methods of managing it can be adopted.
Symptoms of rectocele:
- Feeling of incomplete stool passing: When the rectovaginal septum weakens, instead of the entire stools being pushed down and out, some of it get into the bulge/pocket created when the rectal wall bulges int the vaginal canal. This leaves a persistent sensation that you may not have passed stools completely even after straining.
- Needing to use manual manipulation: To make all the stools pass completely, many women feel the need to apply manual pressure. This involves pressing against the back wall of the vagina or outside on the perineum (the area between the vagina and anus) with clean fingers to guide the stool outwards.
- Feeling of fullness: Some women even feel a heavy sensation or a feeling of a soft bulge protruding inside or out of the vaginal opening. It can often feel more noticeable towards the end of the day or after prolonged standing.
- Constipation and straining: Since rectocele basically creates a pocket in the rectal wall, it can create a vicious cycle of constipation and worsening of the bulge. Stool collects in the rectal wall pocket—which allows stools to settle—stools become hard and dry after settling—makes you strain harder to push them out—wakens the wall further making the rectocele progress—allows more stools to settle in the deepened pocket.
- Discomfort or pain during intercourse (Dyspareunia): Because the front rectal wall bulges into the vaginal canal, penetration can cause discomfort, pressure, or a deep pelvic pain. This often results in reduced sexual satisfaction and anxiety during intimate time.
- Vaginal irritation or bleeding: In more advanced cases where the septal wall bulges near or beyond the vaginal entrance, it can rub against clothing, resulting in tissue irritation, dryness, or minor spotting.
How do childbirth and menopause increase the risk of posterior wall prolapse?
During childbirth and especially after a prolonged labor, due to large birth weight of the baby, or in assisted deliveries using forceps, the intense stretching and physical strain can overstretch or tear the muscles supporting the rectovaginal septum. This disrupts the pelvic floor’s structural support making the back vaginal wall very weak and vulnerable to bending.
As women enter menopause, a significant decline in estrogen levels speeds up structural muscle decline by reducing collagen synthesis and tissue elasticity. The rectovaginal septum thus naturally thins and loses its natural strength over time.
While menopause is a natural transition for all women, those who have also experienced natural or assisted vaginal births face a compound impact on their pelvic floor. When recovery from the physical strain of delivery is incomplete, the combined effect of tissue trauma and menopausal estrogen loss makes the development of a rectocele an understandable and a very common outcome.
What is vaginal splinting and why is it used to assist bowel movements?
- Vaginal splinting is a simple procedure which is used by many women to help completely evacuate stools when they have a rectocele.
- Using clean fingers or gloved fingers, one or two fingers are inserted into the vagina to gently press against the back wall and flatten the rectocele bulge. Alternatively, gentle upward pressure is applied on the perineum to push the stools out and flatten the rectocele.
Why Vaginal Splinting Helps:
When a rectocele forms, stool slips into the bulge instead of moving downward. Splinting acts as a mechanical support that temporarily flattens this pocket and restoring the normal, straight alignment of the rectal wall so stool can pass smoothly. Some simple methods of Splinting:
- Digital Vaginal Splinting: Inserting one or two clean, lubricated fingers into the vagina and pressing gently backward against the posterior wall to flatten the bulge.
- Perineal Support: Applying firm, gentle upward pressure on the perineum (the skin between the vaginal opening and anus) using a hand or clean toilet tissue to support the pelvic floor during evacuation.
- Specialized Assistive Devices: Using commercially available vaginal splinting devices or contoured supports that allow women to apply gentle internal pressure without direct finger insertion, reducing infection risks.
What non-surgical treatments help manage rectocele symptoms effectively?
For many women, conservative measures/non-surgical treatments can help significantly reduce symptoms. They work by preventing the bulge from worsening, and restore comfort during bowel movements.
- High-Fiber Diet: Increasing daily dietary fiber (25–30 grams per day) naturally through whole grains, fruits, vegetables, legumes, and psyllium husk helps create bulkier, softer stools that pass easily without straining.
- Optimal Hydration: When adequate water is paired with fiber, it works excellently to prevent hard stools, thus reducing pressure on the back vaginal wall.
- Stool Softeners: Prescribed osmotic laxatives or stool softeners immensely help constipation during flare-ups.
- Pelvic Strengthening or Kegel Exercises: when taught by a specialized pelvic floor physical therapist, Kegel exercises are powerful in enhancing the overall muscle strength of the pelvic floor.
- Biofeedback Therapy: Using sensors to monitor muscle activity, biofeedback helps women learn how to properly contract and relax the pelvic floor muscles for effective defecation.
- Vaginal Pessaries: A pessary is a removable silicone device inserted into the vagina to provide mechanical support to the weakened pelvic structure. They hold the back vaginal wall in place and thus reduce its bending and bulging.
- Avoid Straining: Refraining from prolonged sitting on the toilet (limiting visits to 3–5 minutes) and avoiding forceful stool movements can help the rectovaginal septum from unwanted pressure.
- Ergonomic Defecation Posture: Using a footstool elevates the knees above the hips. This relaxes the puborectalis muscle and straightens the anal canal for complete stool passage.
Pelvic floor changes including rectocele are one of the most common changes noted in women, especially following childbirth and menopause. Because these symptoms touch on sensitive, personal aspects of health, many suffer in silence out of hesitation or embarrassment to speak about the symptoms they face. However, experiencing a rectocele is a completely natural progression, and is nothing to be awkward about. Seeking medical advice early adds the advantage to opt for gentle, and non-surgical management options like pelvic floor therapy, dietary adjustments, and support devices that can easily relieve discomfort and restore your quality of life.
If you have noticed symptoms like pelvic pressure, difficulty emptying your bowels, or discomfort in your daily routine, do not dismiss it as just episodes of constipation which can be fixed with some laxatives. Come to Smiles institute of gastroenterology to get consults with empathetic colorectal doctors and pelvic floor therapists—under one roof.
Frequently Asked Questions (FAQ):
What causes a rectocele?
The rectum and vagina have two parallel running canals which are separated by a connective tissue called the rectovaginal septum. When this septum gets weakened due to childbirth, menopause, trauma from previous surgeries, it can bend or bulge instead of remaining straight. When the front rectal wall bulges into the back vaginal wall, it is called a rectocele.
Does rectocele cause back pain?
Yes, a rectocele can cause back pain. But it is more of a secondary symptom which occurs along with other primary symptoms like pelvic pressure, or straining during stools. The pelvic floor muscles often co-ordinate to support the pelvic organs. when the rectovaginal septum weakens, other pelvic muscles can sometimes put in the extra effort to keep organs in place, which can cause the lower back pain.
How can rectocele be treated?
A rectocele can be treated through both non-surgical and surgical options depending on the severity of your symptoms. Mild to moderate cases often can be managed through approaches like a high-fiber diet, pelvic floor physical therapy, and supportive vaginal pessaries. For severe or persistent cases that significantly impact daily life, a minor surgical repair can reinforce the weakened wall between the vagina and rectum to permanently restore proper anatomical support.
How is a rectocele repaired?
A rectocele repair surgery called posterior colporrhaphy, is performed by accessing the weakened wall through the vagina without any external abdominal cuts. The surgeon brings together and stitches the stretched rectovaginal septum back into place to strengthen the support between the rectum and vagina. This closes the bulge and straightens the rectal canal which helps bowel movements pass smoothly again.
How to poop if you have a rectocele?
Passing stools comfortably with a rectocele relies on using proper posture, avoid straining, and applying gentle support when needed. You can use these three techniques if you feel you have a rectocele:
- Use footstools: Elevate your feet on a footstool with your knees above your hips to straighten the rectal canal for easier passage of stools.
- Practice splinting: Gently press clean fingers against the back wall of your vagina or apply upward pressure on the perineum to flatten the bulge and direct stool outward.
- Keep stools soft: Ensure your stool stays soft with daily fiber and plenty of water so you do not have to strain or apply pressure during stool movements.
